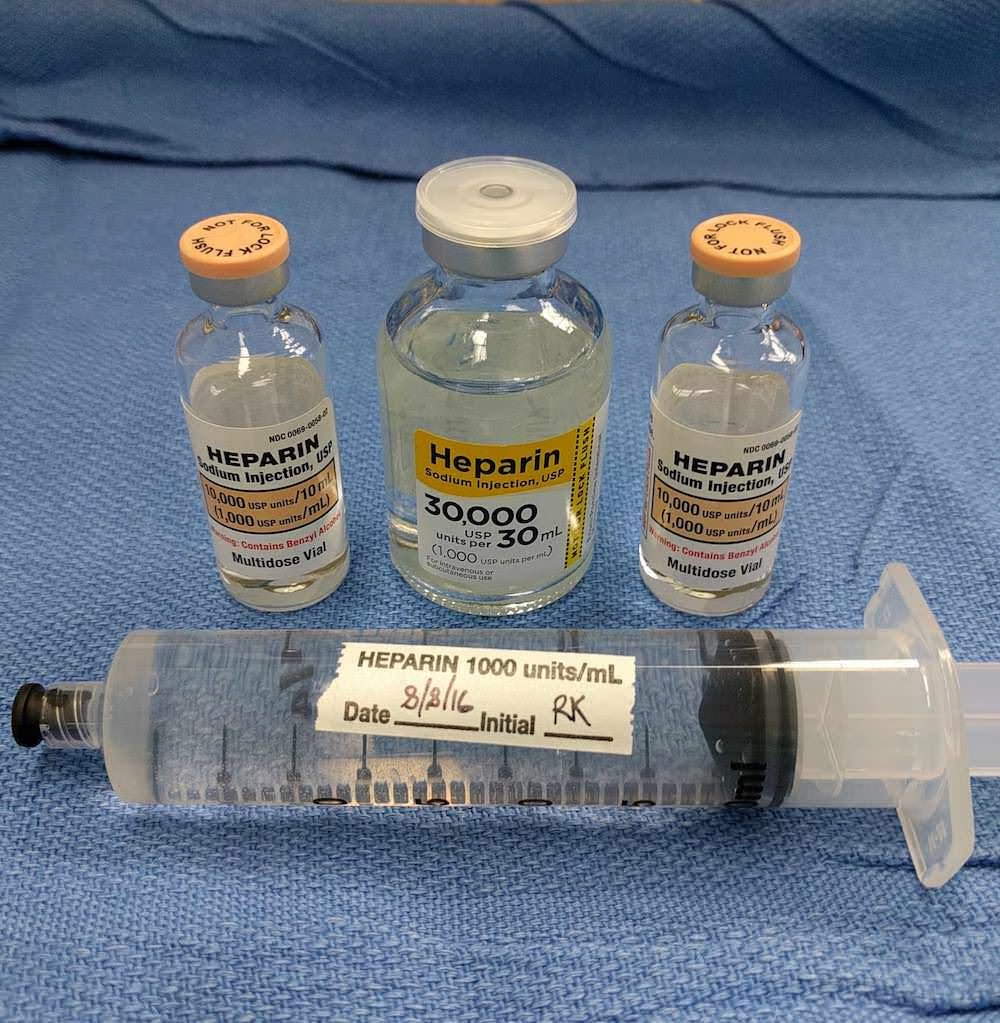
To minimize the risk of thrombosis on the heart-lung machine, 3-4 mg/kg IV heparin boluses are administered to patients prior to initiating cardiopulmonary bypass. Many institutions also test for adequate heparinization before going on pump using a target activated clotting time (ACT) > 480 seconds. In such large doses, much of the heparin is redistributed across tissues and binding proteins in addition to the “central compartment.” These large doses also extend heparin’s typical, apparent half-life from ~ 30 minutes to > 2 hours.
Heparin anticoagulation is reversed with protamine sulfate (typically in a 1:1 dosage) which has an apparent half-life of ~5 minutes. Logically, protamine will neutralize all of the free fraction of heparin readily accessible in the central compartment, but due to its much shorter half-life, protamine will be cleared before eliminating all of the biologically active heparin gradually liberated from binding proteins. This is the proposed mechanism of heparin rebound.
To mitigate this re-heparinization, many anesthesiologists give 50-100 mg of additional protamine just before chest wiring. The literature also references protamine infusions running for hours post-bypass to continuously neutralize any heparin rebound even outside of the operating room.
Thus far, I have been giving an extra protamine bolus with fascial closure and rechecking an ACT prior to leaving the room. Maybe I’ll change my technique during fellowship. :-)
The differential for bleeding after cardiopulmonary bypass is incredibly vast. Unidentified surgical bleeding, dilutional coagulopathy, qualitative/quantitative platelet defects, hypothermia, hypocalcemia, and heparin rebound are just some things to consider and correct.




Leave a Reply