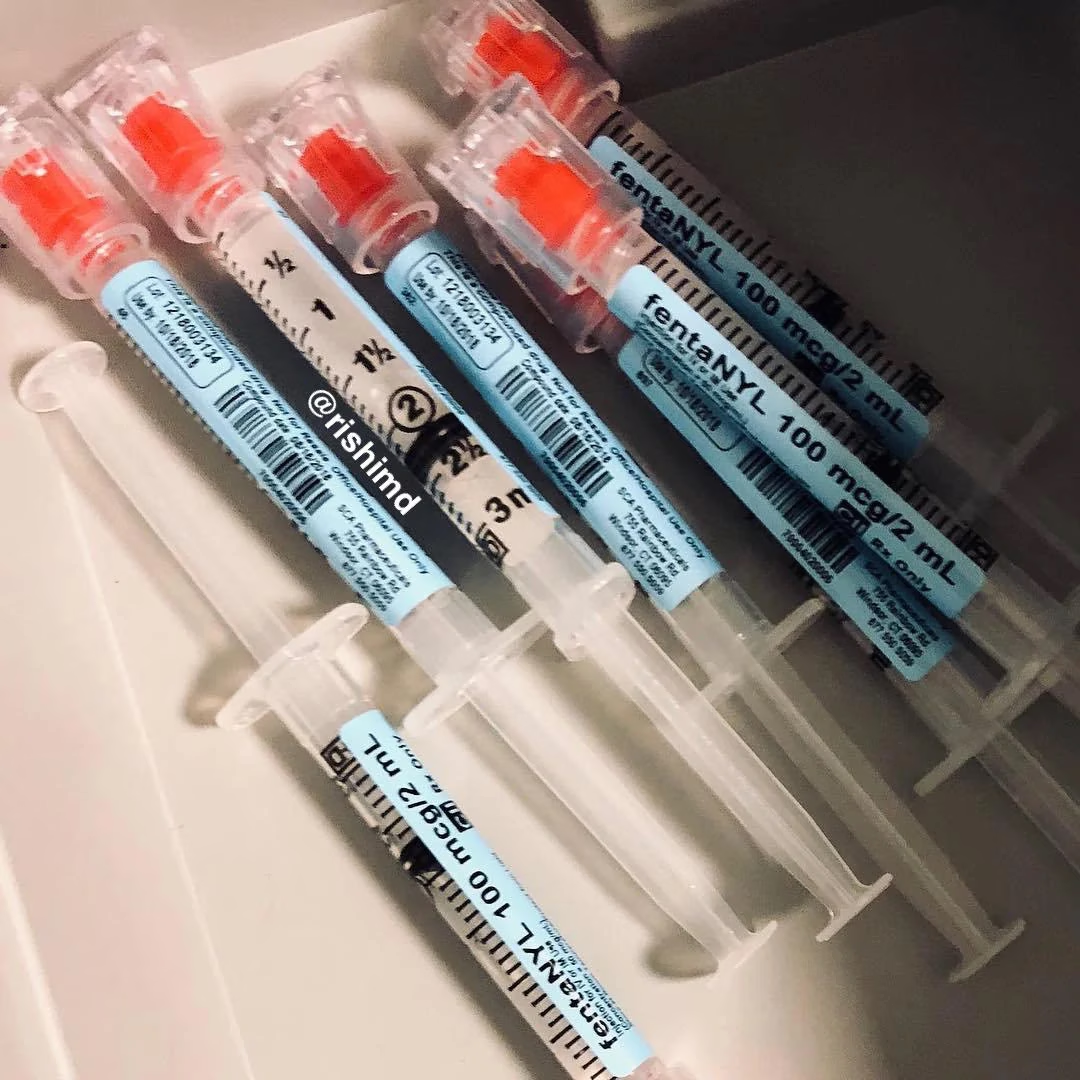
Fentanyl (Sublimaze) is the most common synthetic narcotic I administer in the OR and the ICU. It is ~100x more potent than morphine and associated with many of the same side effects as other mu-opioid agonists – nausea, vomiting, constipation, respiratory depression, hallucinations, and sedation. Fentanyl can be delivered through several routes: intravenous, intrathecal (off-label), transdermal (fentanyl patch), intranasal, sublingual, and as a lozenge (“fentanyl lollipops”). Many of these routes are possible due to the medication’s highly lipophilic nature.
For ~50 years, fentanyl has come under fire for its dangers in recreational use. Often times, patients are shocked when they receive fentanyl intraoperatively, in the PACU, or in the ICU given its societal stigma; however, from a clinical/therapeutic standpoint, this medication offers several advantages – clean metabolite profile, inexpensive, relatively short bolus half-life (keep in mind that the context-sensitive half-life increases drastically after ~2-3 hours of infusion), lack of histamine release, etc.
Depending on the surgery, I’ll routinely give anywhere from 100 mcg to over 1000 mcg of fentanyl for analgesia and as an general anesthetic adjunct. I use it in tandem with agents like propofol and ketamine for bedside procedures in the ICU (bronchoscopy, chest tube placement, vac changes) and, despite how much I hate running narcotic DRIPS, as a form of sedation for mechanical ventilation. I also consider a predictable form of “rescue analgesia” for patients with intractable pain.
Drop me comments with questions below! :-)




Leave a Reply