Blood conservation strategies are routinely employed in cardiac surgery to minimize the overall need for transfusions. Techniques such as Cell Saver, retrograde autologous priming (RAP) of the cardiopulmonary bypass (CPB) circuit, utilizing CPB tubing that requires less priming, and intraoperative autologous blood donation (IAD) with the isolation of platelet-rich plasma (PRP) are all methods I’ve employed in my practice.
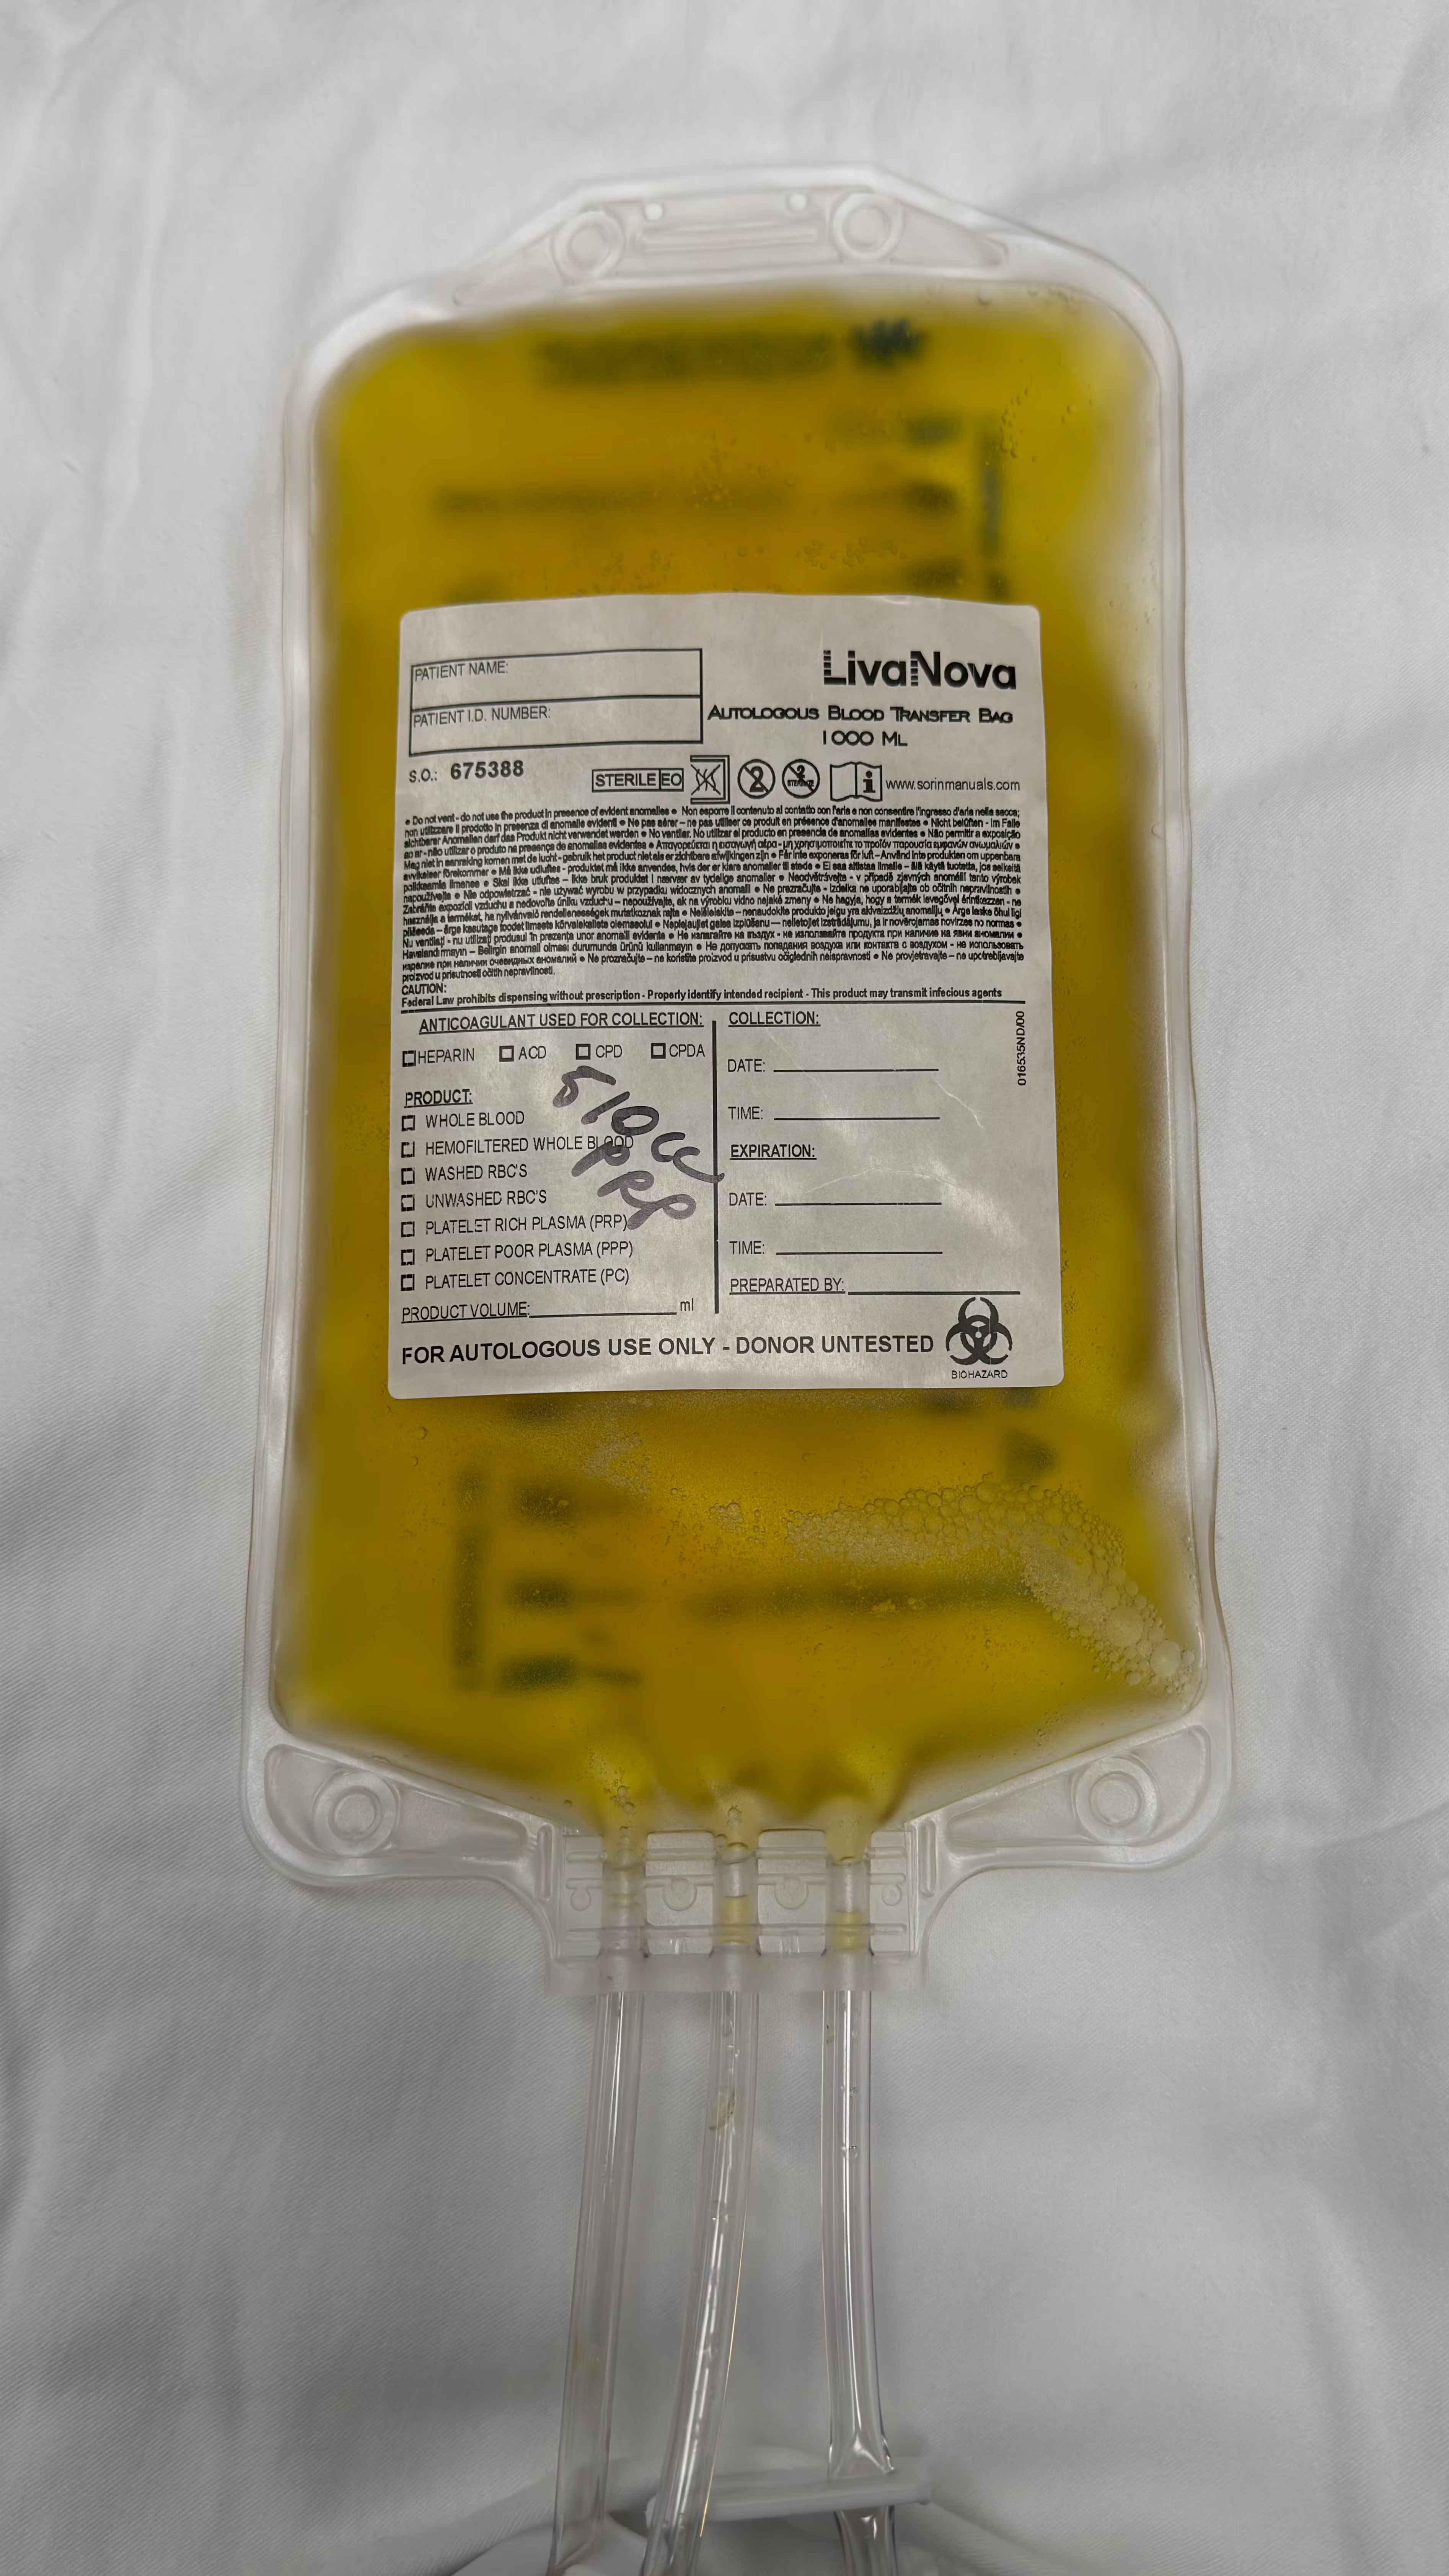
The concept behind IAD is straightforward: drain the patient’s whole blood before surgery and reinfuse crystalloid to maintain intravascular volume. In a sense, this “dilutes out” a patient’s blood volume, so when they lose blood during surgery, they are losing fewer red blood cells per unit volume of fluid lost (acute normovolemic hemodilution). In patients with normal hematocrits, I’ll drain up to a liter of whole blood via a central line into a bag with citrate to prevent coagulation. At that point, my perfusionist colleagues work their magic by spinning down the whole blood into Cell Saver (packed RBCs) and platelet-rich plasma (PRP).
Cell Saver can be used on CPB or after coming off bypass as fluid resuscitation in the form of the patient’s own red blood cells. Additionally, since platelet dysfunction is universally expected after cardiopulmonary bypass with hypothermic arrest, I’ll reinfuse the PRP post-bypass as well.
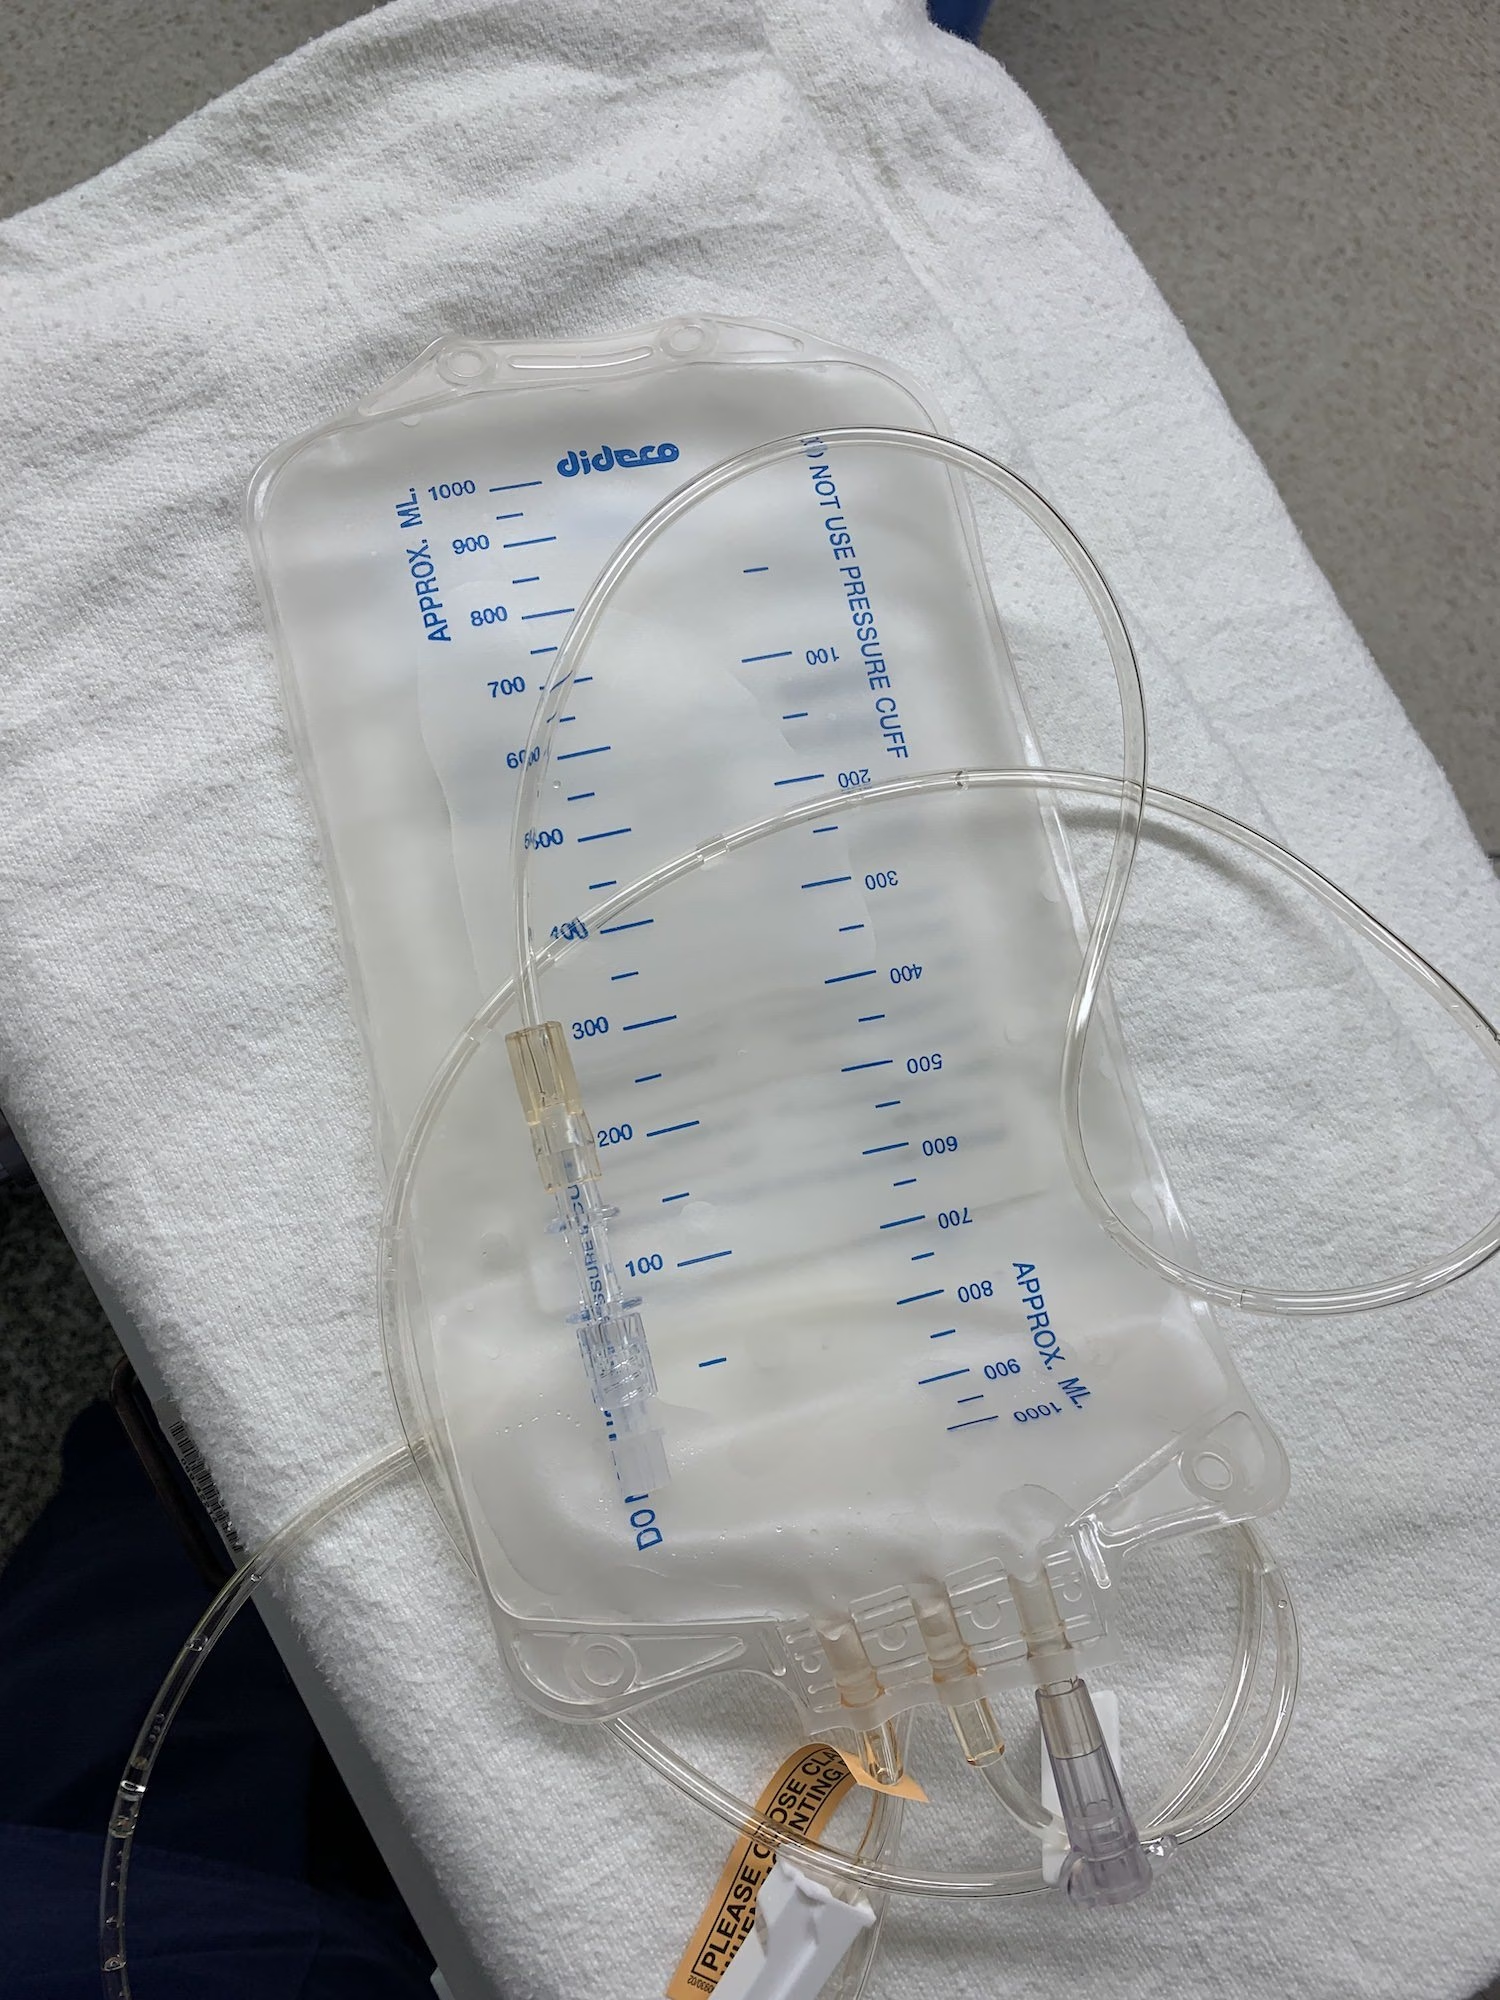
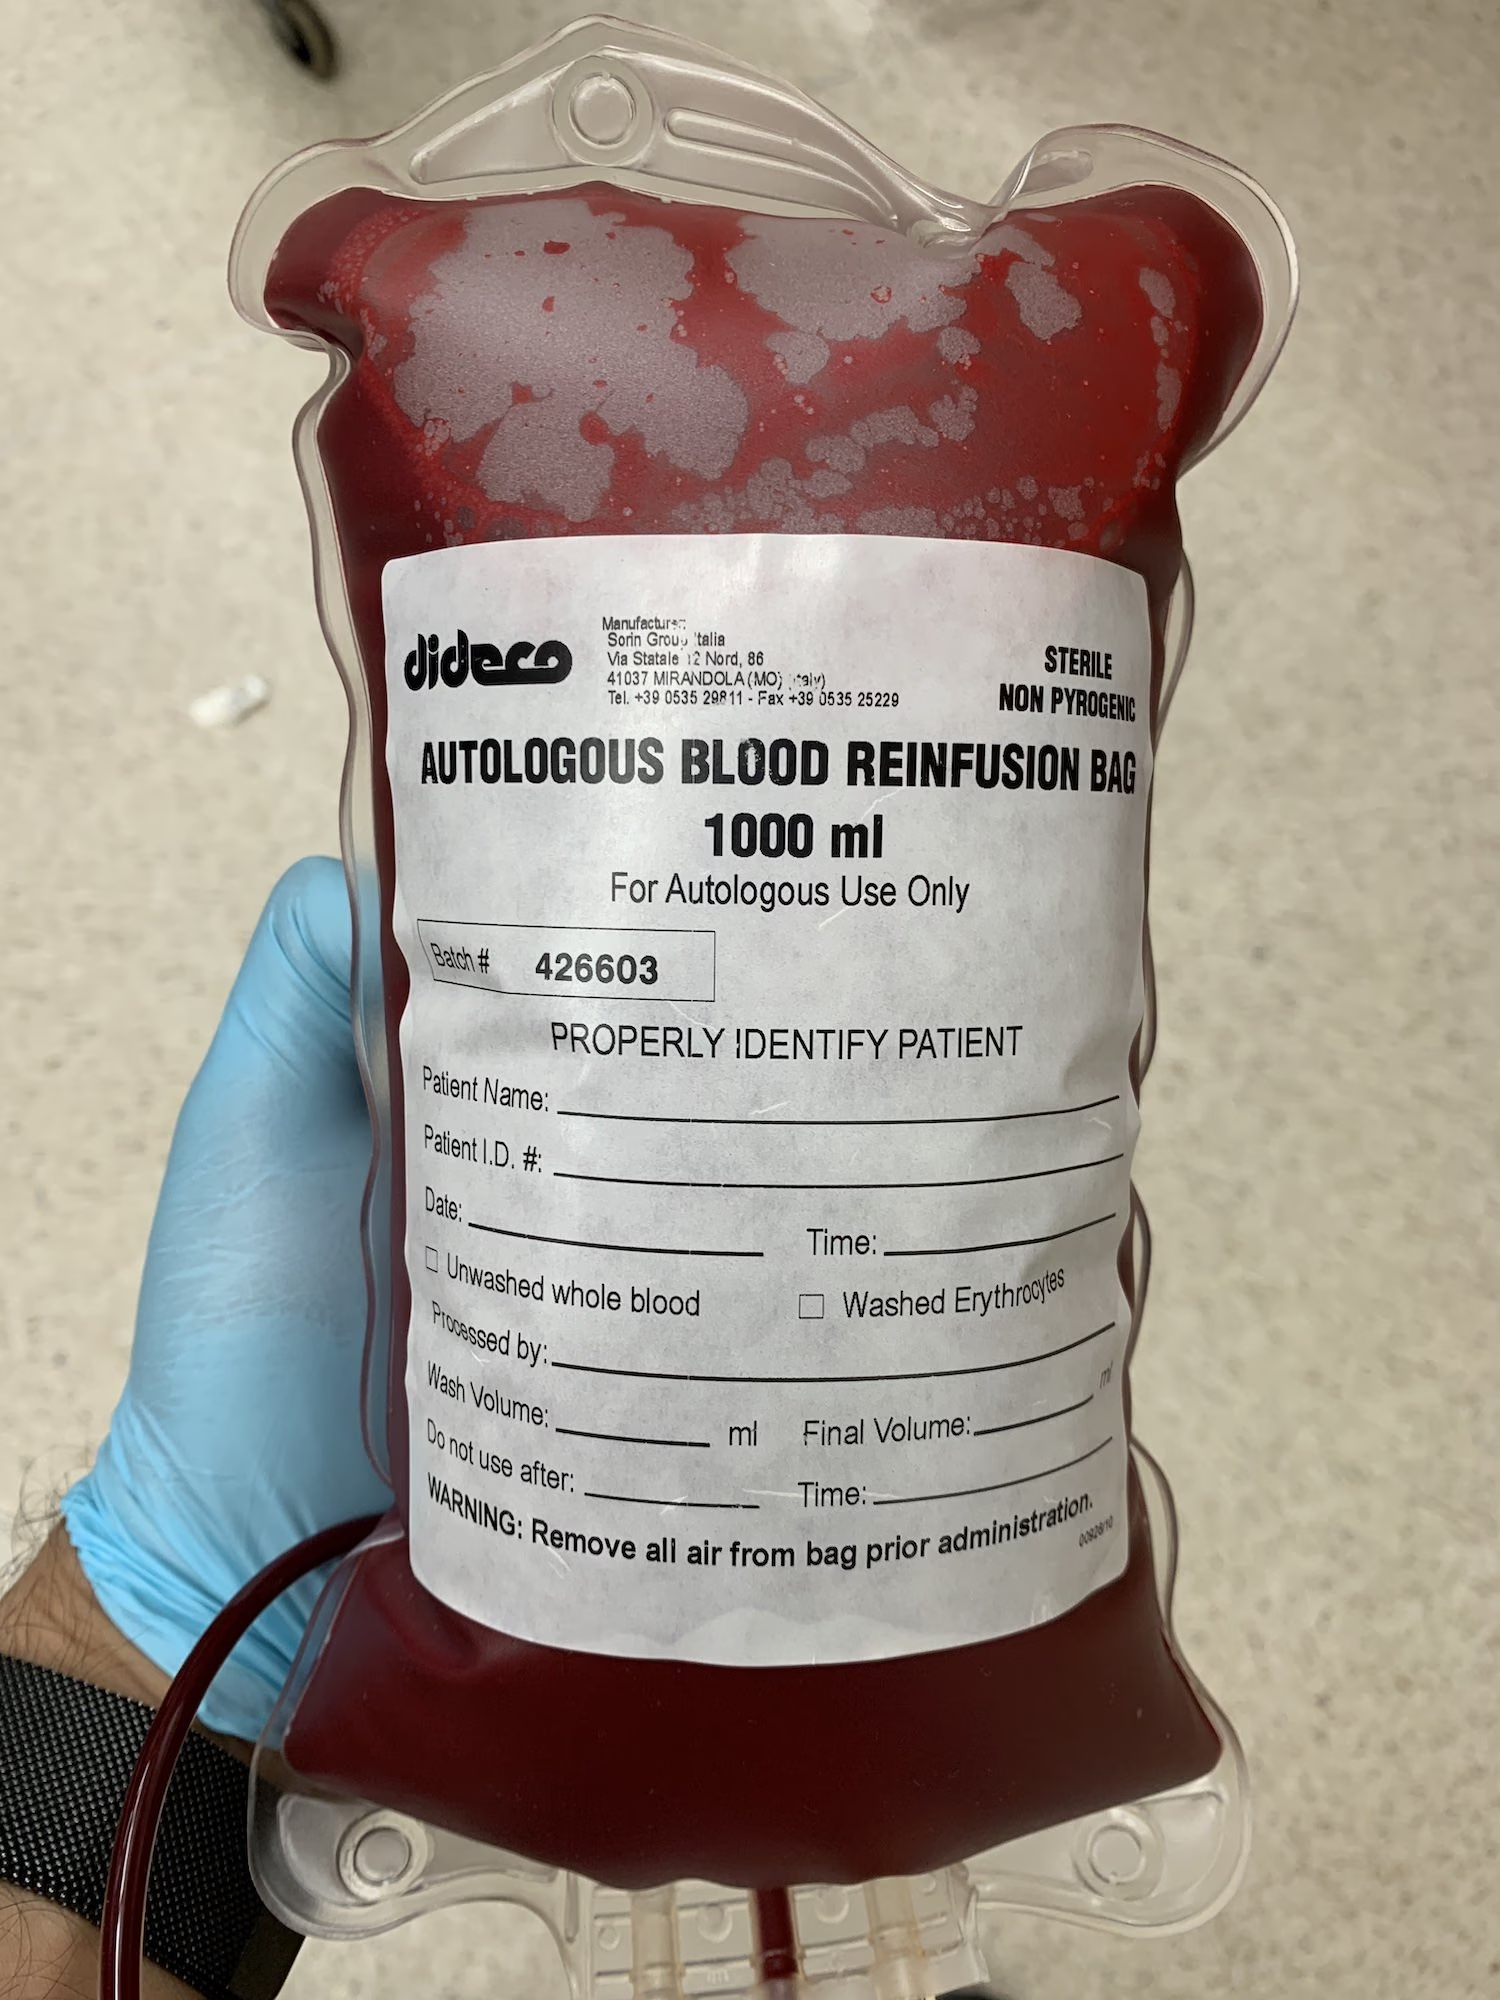
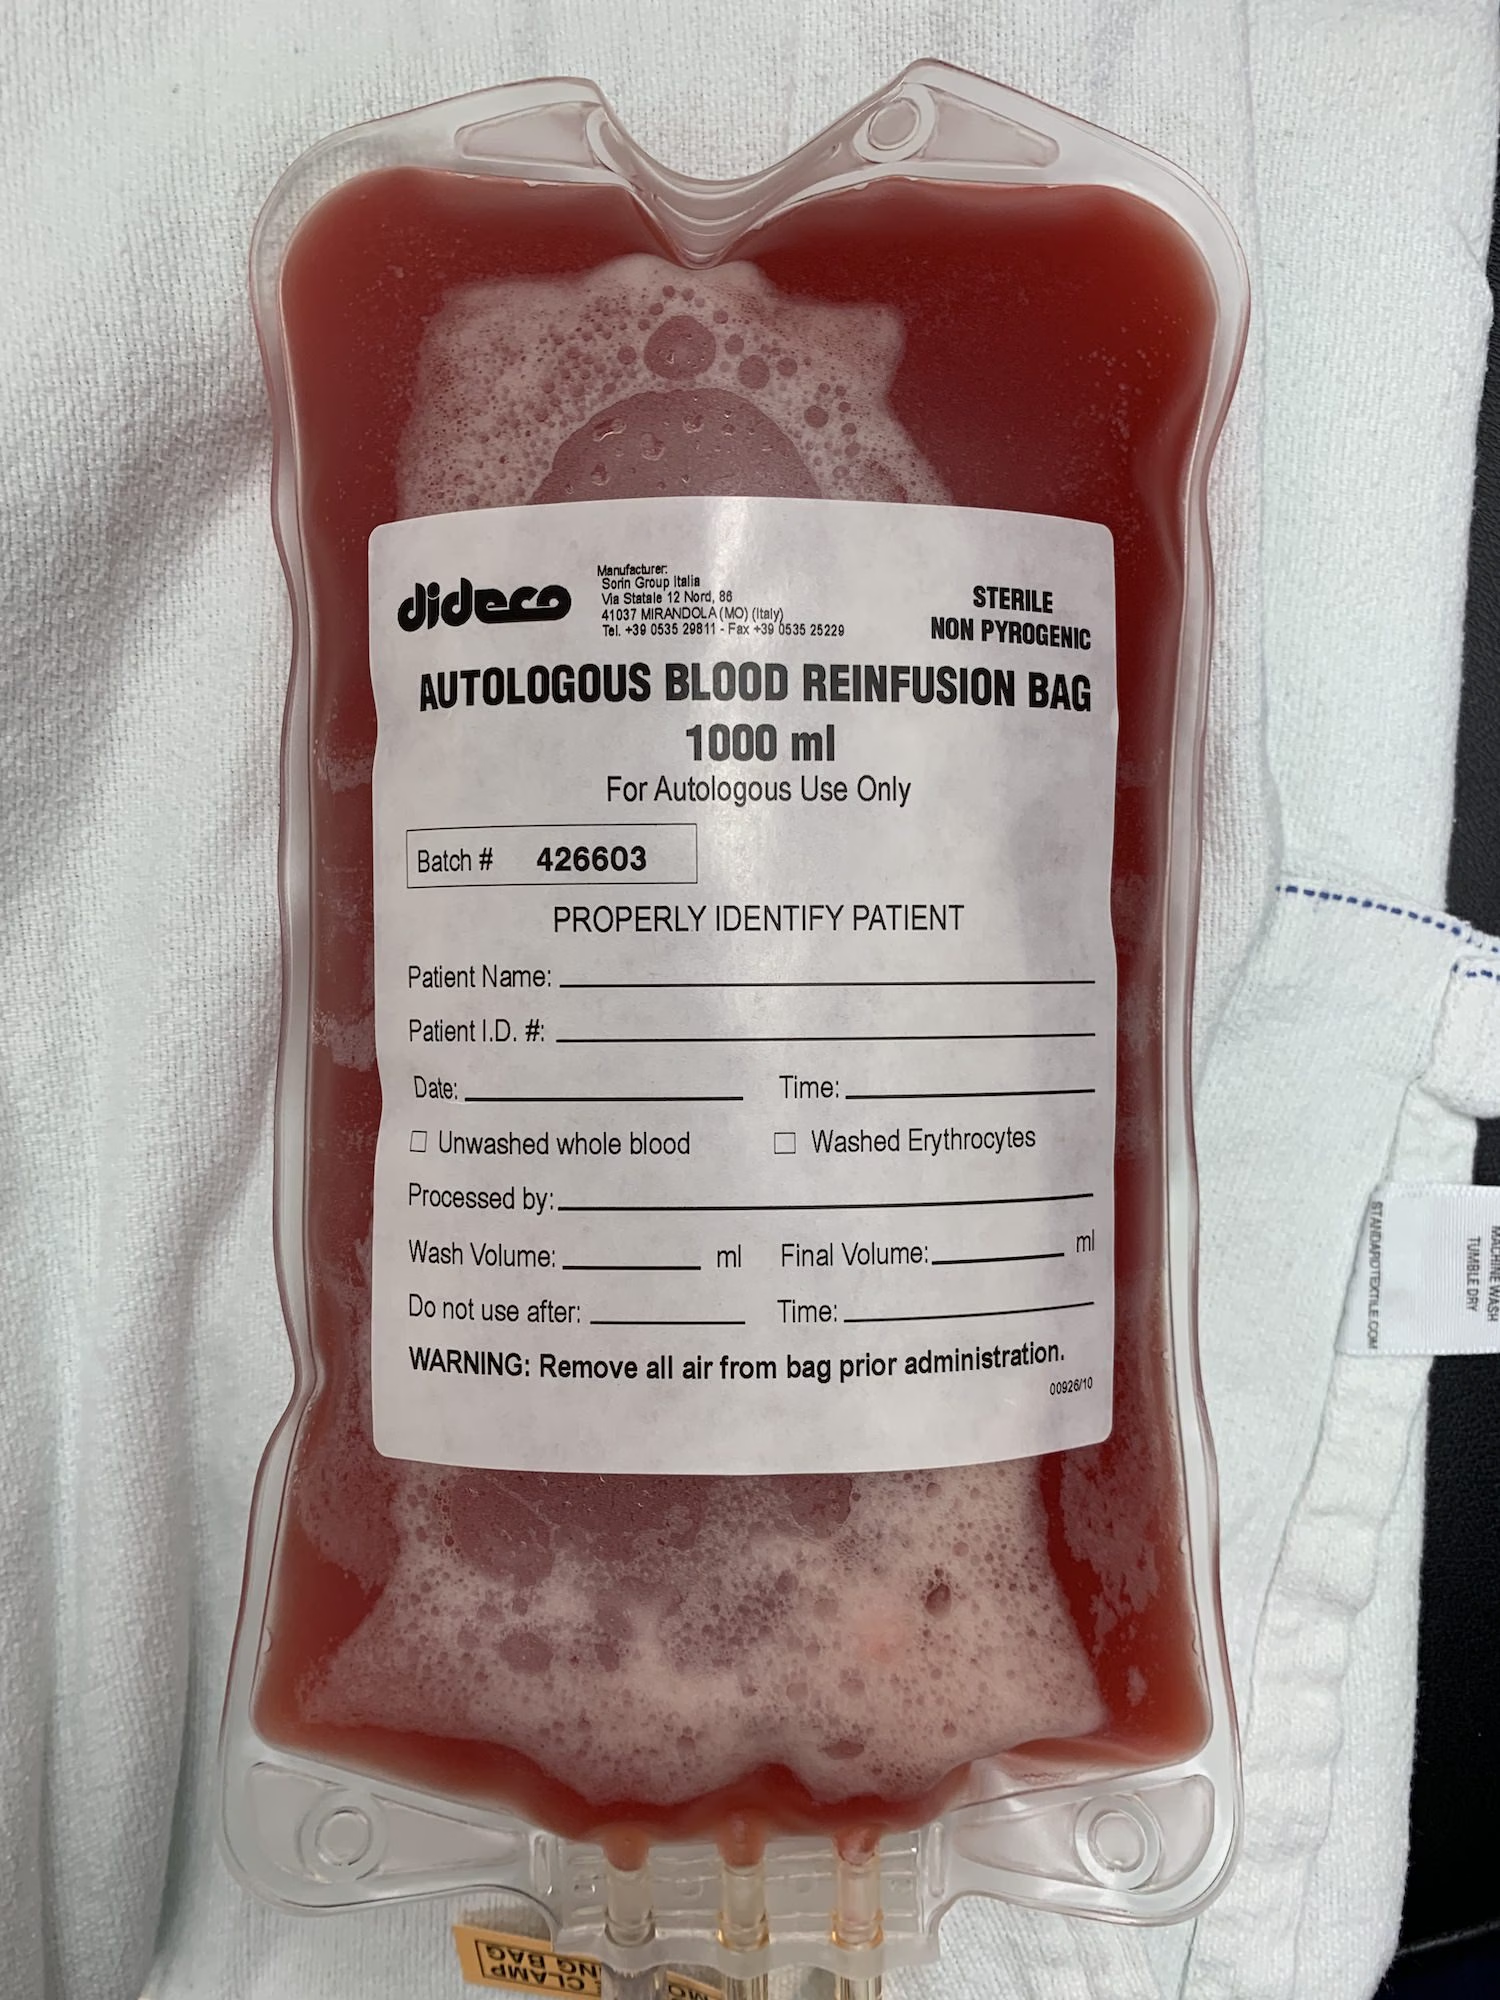
Here’s another example of what aPRP looks like (when there are less red blood cells in the mix!)
Drop me a comment below with questions! :-)




Leave a Reply