• Hypophosphatemia

    Hypophosphatemia

    Phosphate is crucial for cellular/energy metabolism, bone integrity, and various enzymatic processes. Hypophosphatemia is classified as mild (2.5-3 mg/dL), moderate (1-2.5 mg/dL), or severe (<1 mg/dL, up to 30% all-cause mortality!) based on serum concentration. Mechanisms of hypophosphatemia include transcellular shifting (refeeding syndrome, insulin administration, alkalosis), renal losses (primary hyperparathyroidism,…

    Read More

  • Desmopressin (DDAVP) Clamp

    Desmopressin (DDAVP) Clamp

    Patients with severe hyponatremia ([Na+] < 120 mEq/L) can present with altered mentation, seizures, lethargy, and even coma. After identifying the likely cause(s), treatment is centered around a combination of sodium replacement (usually with 3% hypertonic saline, HTS) and volume correction depending on if the patient is hypo-, eu-, or…

    Read More

  • Hyponatremia Correction For Hyperglycemia

    Hyponatremia Correction For Hyperglycemia

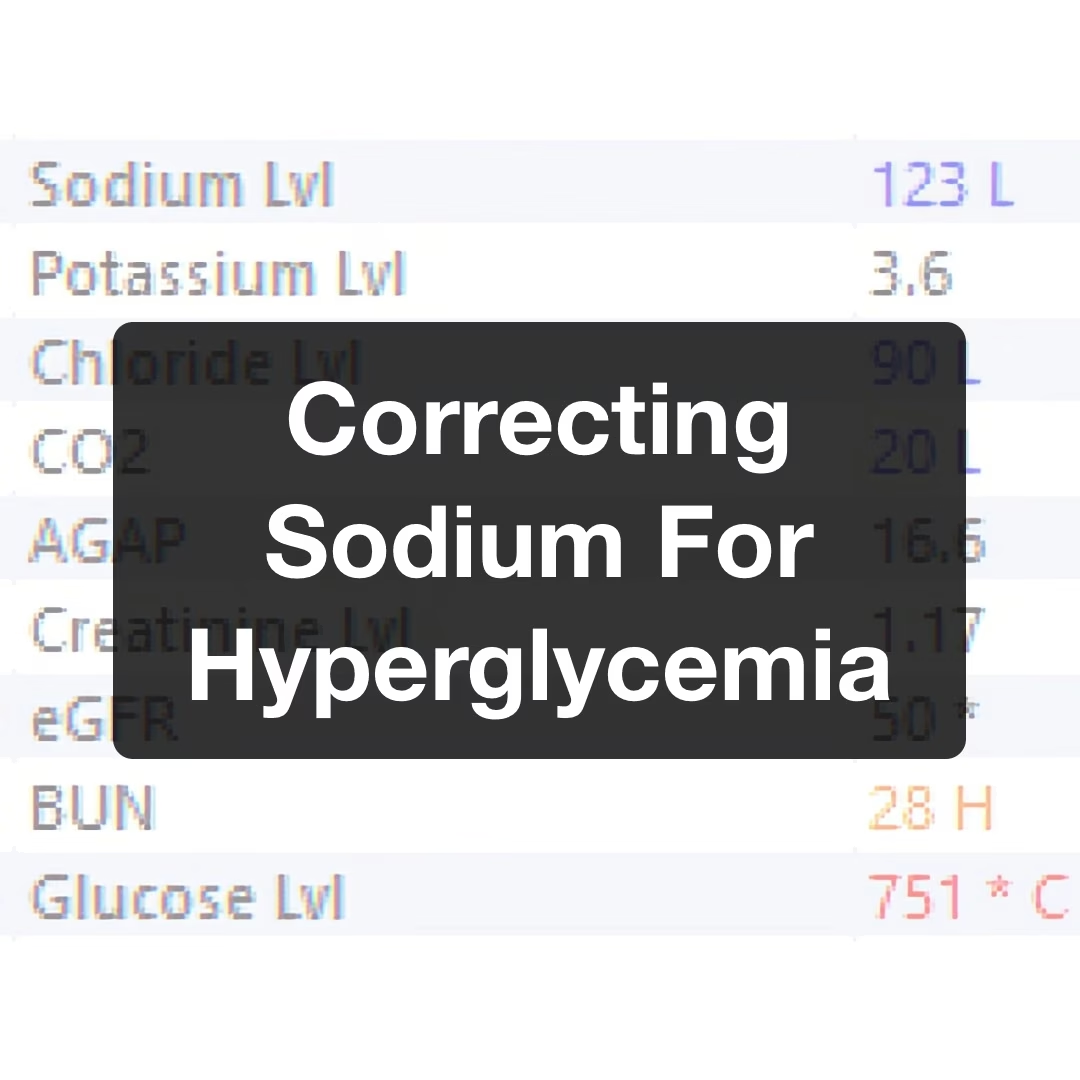
    Sodium is the primary cation (positive-charged ion) in the extracellular space. Therefore, dilutional hyponatremia can occur if free water is added to the extracellular space from fluid shifts and infusions. Let’s look at this basic metabolic profile. Glucose 751 mg/dL (critically high). Sodium 123 mEq/L (low). Hyponatremia is an expected…

    Read More

  • Hypernatremia And Free Water Deficit

    Hypernatremia And Free Water Deficit

    Sodium (Na) fluctuations portend increased in-hospital death for ICU patients, and when working them up, it’s essential to determine if these disorders are acute or chronic (> 48 hours or unknown duration). For hypernatremia ([Na] > 145 mEq/L), think about situations where there is a free water deficit (FWD) –…

    Read More

  • Total Calcium Versus Ionized Calcium

    Total Calcium Versus Ionized Calcium

    Calcium is traditionally reported as a total serum concentration (i.e., complete metabolic profiles) and ionized calcium concentration (i.e., blood gases). To interpret these labs, one must understand what they represent. Under normal physiologic conditions, roughly 50% of calcium is bound (primarily to albumin), and 50% is ionized (the biologically active…

    Read More

  • Lactated Ringers And Normosol In Hyperkalemia

    Lactated Ringers And Normosol In Hyperkalemia

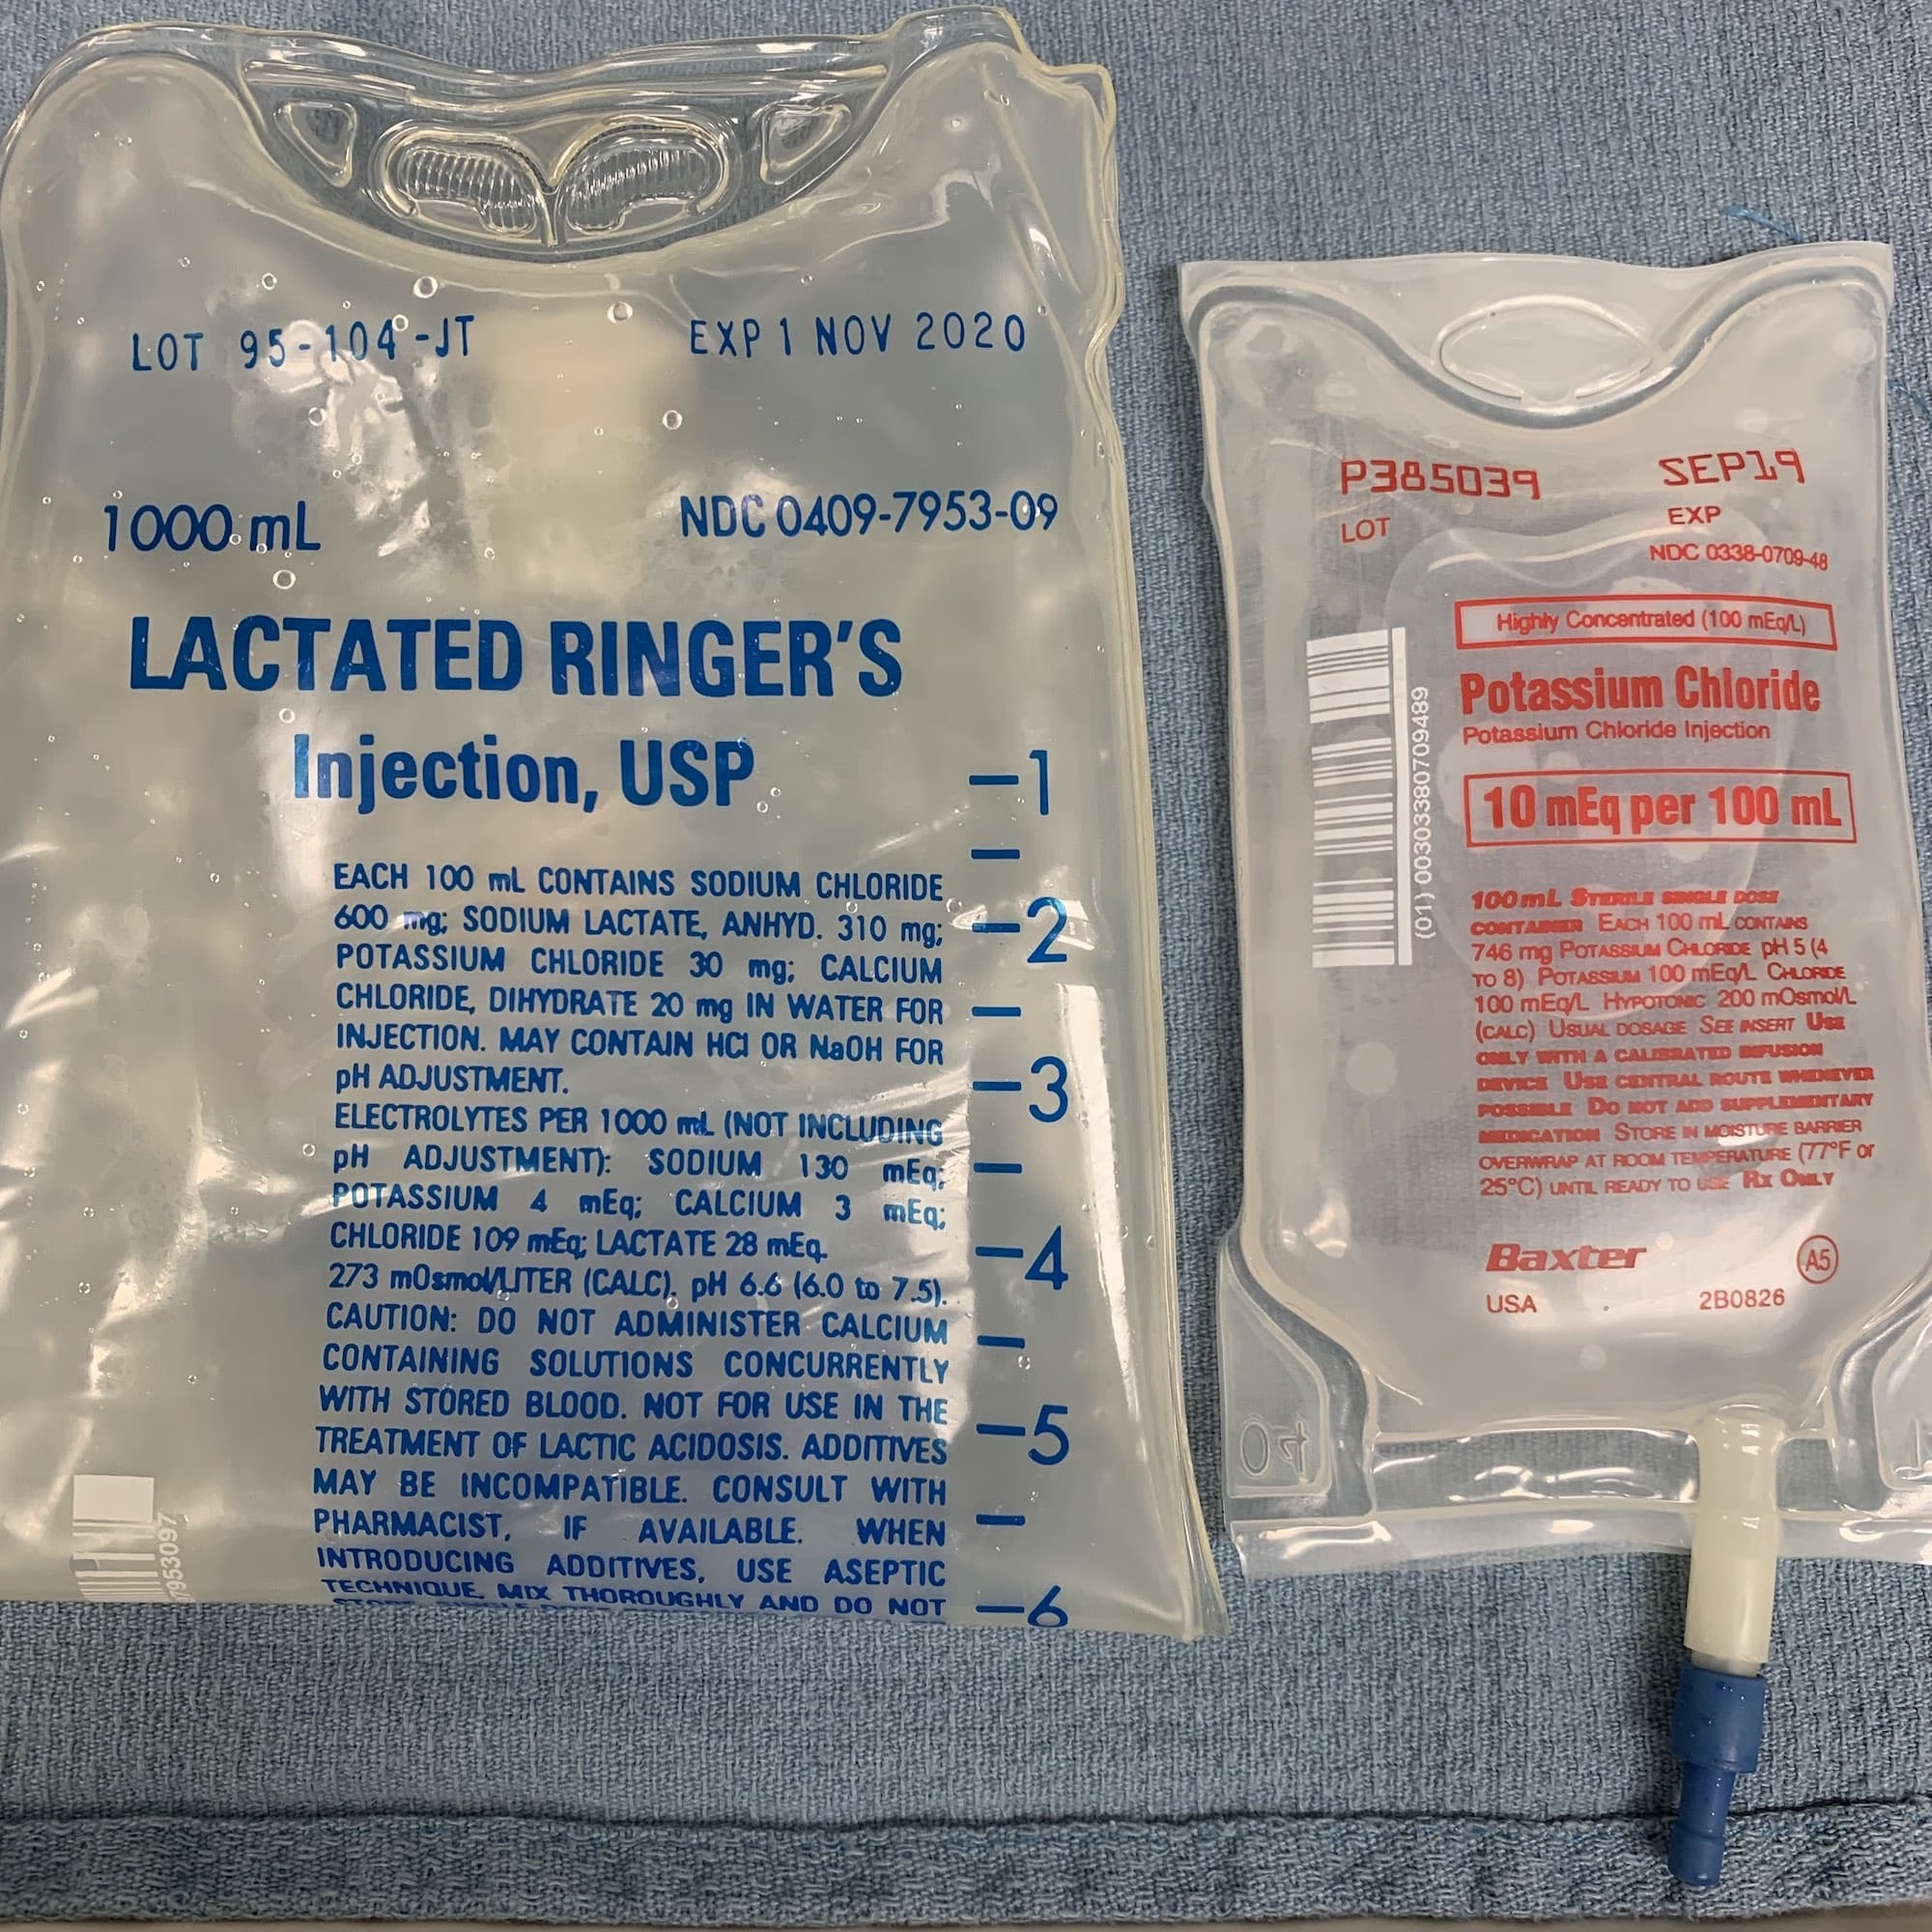
    As an intensivist and anesthesiologist, I spend considerable time pondering the physiology and evidence for practices and questioning dogma rampant in the ICU/OR settings. I’ve heard one recurrent theme: the fear of using Lactated Ringers (LR) and Normosol in patients with renal impairment. Why? Because they both contain potassium (K+),…

    Read More

  • Magnesium Sulfate

    Magnesium Sulfate

    Magnesium is an important intracellular electrolyte that regulates neuronal conduction, vascular tone, myocardial excitation, and muscular contraction. Patients often lose magnesium through significant NG tube drainage, diarrhea, and diuresis. Many of them also come in with baseline malnutrition secondary to poor absorption and alcoholism.As a med student/resident, I saw magnesium…

    Read More

  • Calcium Chloride

    Calcium Chloride

    Calcium chloride (CaCl2) is an ionic form of intravenous calcium repletion with roughly three times more bioavailable calcium than its organic counterpart – calcium gluconate.

    Read More

  • Potassium Chloride

    Potassium Chloride

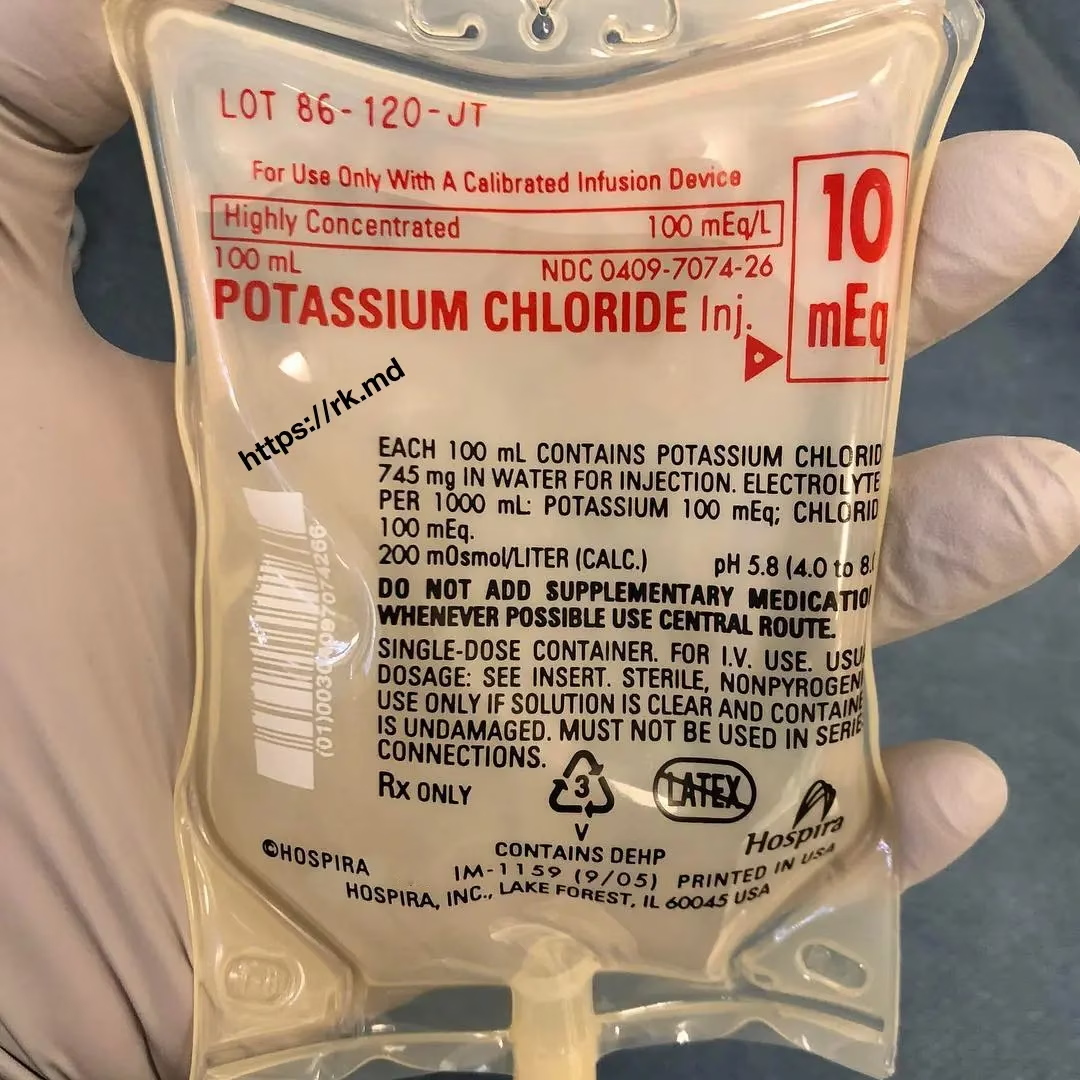
    Potassium chloride (KCl) is a form of intravenous electrolyte repletion in hypokalemia – the most common electrolyte disorder in hospitalized patients often caused by diarrhea, vomiting, loop/thiazide diuretics, steroids, and poor intake among many other etiologies.

    Read More